
Independent physician groups often talk about physician time as if the primary constraint is clinical capacity.
It is not.
Physician time is also consumed by hiring decisions, staffing issues, vendor questions, scheduling conflicts, operational approvals, financial tradeoffs, partner concerns, workflow problems, and countless other matters that accumulate over time.
Some of those decisions genuinely require physician judgment.
Many do not.
The challenge is knowing the difference.
Not Every Important Decision Is a Physician Decision
One reason physician leaders become overwhelmed is that “important” and “requires a physician” are often treated as the same thing.
They are not.
A decision can be consequential without requiring clinical expertise or physician ownership.
For example:
- Selecting between two vendors may matter financially, but it may not require a physician.
- Deciding how to structure a scheduling workflow may affect patient access, but the operating team may be better positioned to own it.
- Reviewing routine staffing decisions may feel important, but a well-designed management structure should not require physician involvement in every hire.
- Resolving an operational problem may have clinical implications, but that does not necessarily mean a physician must lead the entire process.
The right question is not:
“Is this important?”
It is:
“What part of this decision truly requires physician judgment?”
Physician Judgment Should Be Used Where It Adds Unique Value
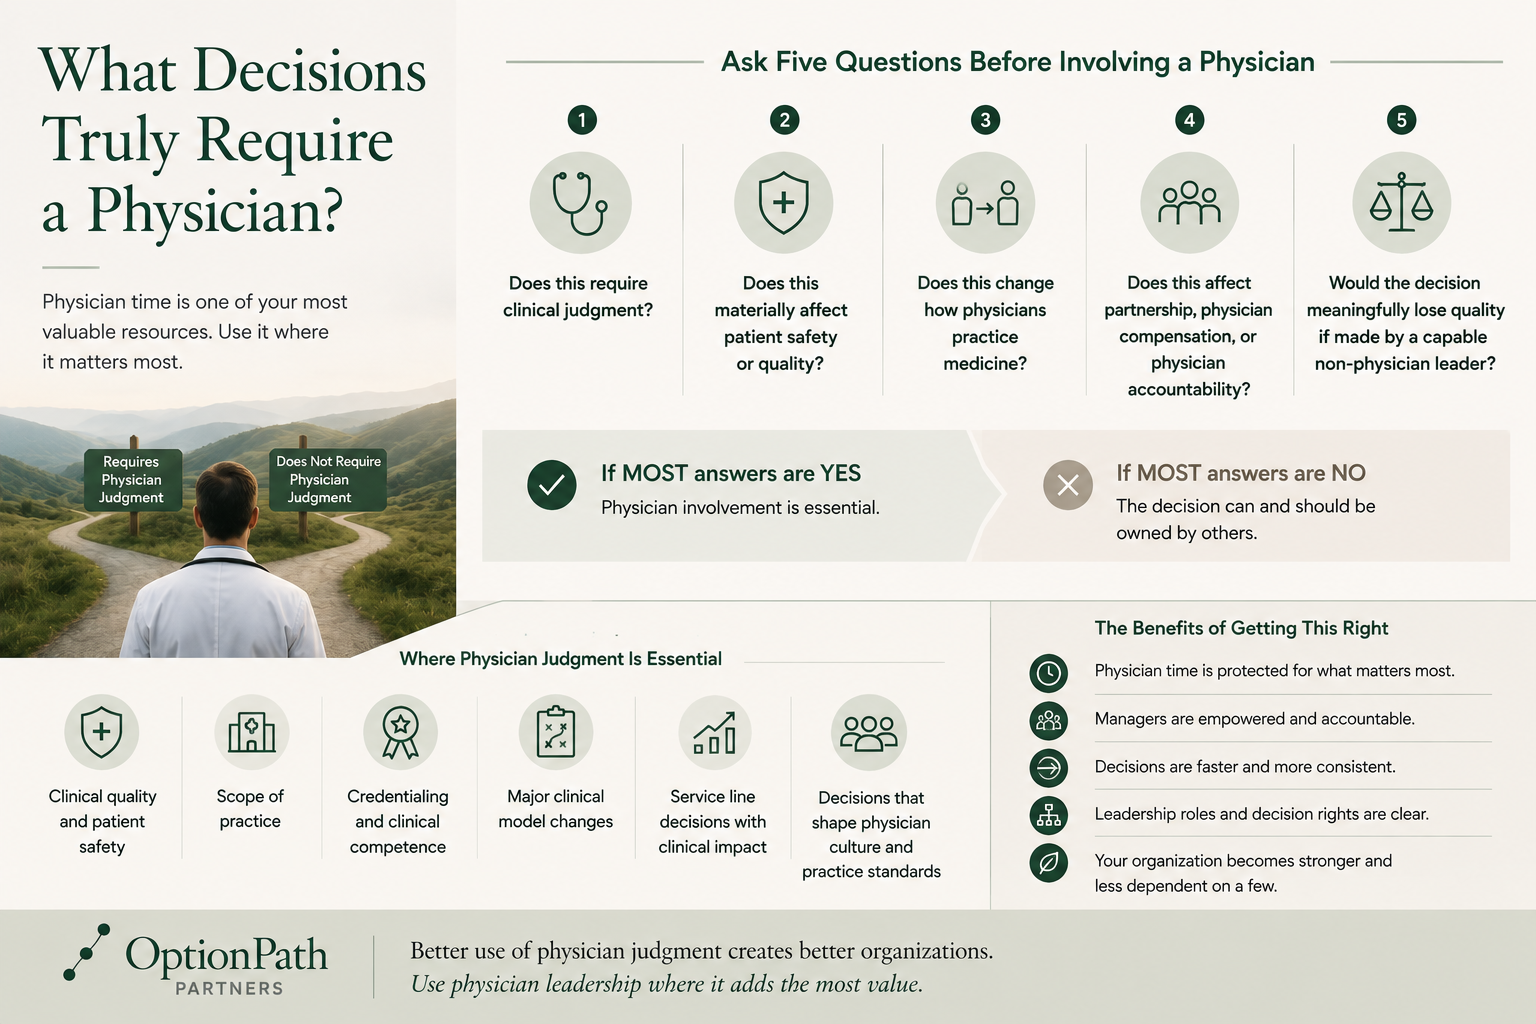
There are decisions where physician involvement is essential.
These usually include matters such as:
- Clinical quality and patient safety
- Scope of practice
- Care delivery standards
- Physician credentialing and clinical competence
- Major clinical model changes
- Significant service-line decisions with direct clinical implications
- Decisions that materially affect physician culture, partnership, or medical practice standards
In these areas, physician judgment is not simply helpful. It is central.
But even then, physician involvement does not necessarily mean physician ownership of every step.
A physician leader may define the clinical standard while management designs the workflow.
A physician may set the criteria while others execute the process.
A physician group may establish the strategic direction while an operating leader evaluates vendors, timelines, and implementation.
That distinction protects physician capacity without diminishing physician authority.
The Default Administrator Problem
In many independent groups, physicians become the default administrators because the organization never explicitly designed an alternative.
A physician partner becomes involved because:
“Someone has to decide.”
Then the pattern repeats.
Over time, that physician becomes the person who approves staffing exceptions, resolves scheduling conflicts, reviews contracts, answers operational questions, and steps into problems whenever ownership is unclear.
That may work when the practice is small.
As the organization grows, it becomes a structural problem.
The physician is not necessarily involved because the work requires physician judgment.
The physician is involved because the operating model has failed to assign responsibility elsewhere.
Decision Rights Matter
A stronger organization defines decision rights explicitly.
For each recurring decision, leadership should understand:
Who recommends?
Who decides?
Who needs to be consulted?
Who needs to be informed?
That sounds simple, but many practices operate with none of these roles clearly defined.
The result is predictable.
Too many decisions move upward.
Too many physicians become involved.
Management waits for approval.
Routine matters become leadership matters.
And physician capacity is consumed by decisions that should have been resolved elsewhere.
A Useful Test
Before involving a physician in a decision, ask five questions:
- Does this require clinical judgment?
- Does this materially affect patient safety or quality?
- Does this change how physicians practice medicine?
- Does this affect partnership, physician compensation, or physician accountability?
- Would the decision meaningfully lose quality if made by a capable non-physician leader?
If the answer to the first four is no and the fifth is also no, the physician may not need to own the decision.
That does not mean physicians should be excluded.
It means their role should be intentional.
Protecting Physician Time Is a Leadership Responsibility
Physician capacity should be treated like any other scarce strategic resource.
If physicians are spending hours every week on work that does not require them, that is not merely a personal productivity issue.
It is an organizational design issue.
The practice should examine:
- whether decision rights are clear
- whether management has sufficient authority
- whether leaders have the capability to make the decisions assigned to them
- whether processes are overly centralized
- whether physicians are stepping in because trust is low
- whether recurring issues reveal a deeper structural problem
The goal is not to remove physicians from leadership.
The goal is to use physician leadership where it matters most.
Better Use of Physician Judgment Creates Better Organizations
Independent physician groups need physician leadership.
They do not need physicians to personally carry every important decision.
When physician judgment is reserved for the areas where it adds unique value, several things happen.
Physicians regain time.
Managers become more accountable.
Decisions move faster.
Leadership roles become clearer.
And the organization becomes less dependent on a handful of physician owners to keep everything moving.
That is not reducing physician influence.
It is strengthening it.
The question is not whether physicians should lead.
The question is where their judgment is truly indispensable.
Michael Isaacs
Leave a Reply